



The influencing factors and development of a prediction model for postoperative enteral nutrition intolerance in colorectal cancer
-
摘要:
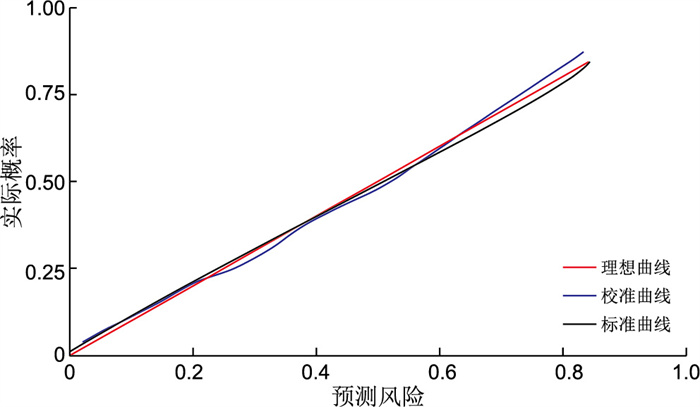
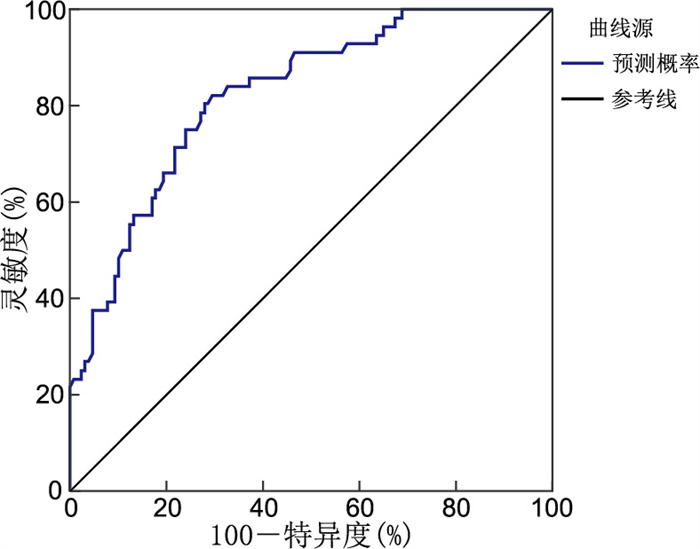
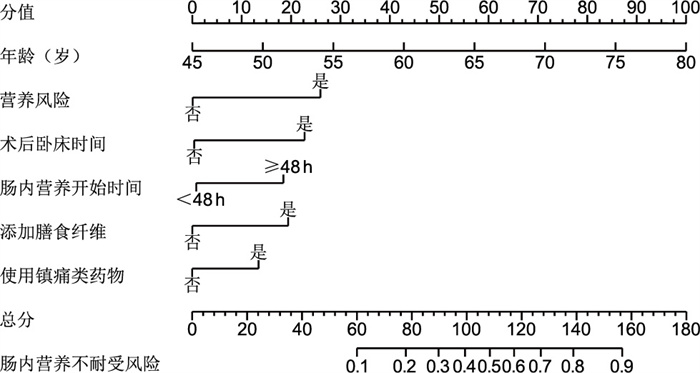
目的 构建结直肠癌术后肠内营养不耐受发生风险的预测列线图模型,并对该模型的预测效能进行初步验证。 方法 回顾性选取2021年1月—2024年6月在东部战区总医院行手术治疗的185例结直肠癌患者作为研究对象,患者术后均给予肠内营养支持,根据患者是否出现不耐受症状,分为耐受组(129例)和不耐受组(56例)。收集2组患者的临床资料,包括人口学指标、结直肠癌病情、手术资料及术后肠内营养相关情况等。采用多因素logistic回归分析筛选影响结直肠癌术后肠内营养不耐受的因素,根据筛选出的相关因素构建列线图预测模型,采用ROC曲线及校准曲线对模型的区分度和校准度进行验证。 结果 年龄大、有营养风险、术后卧床时间≥3 d、肠内营养开始时间≥48 h及使用镇痛类药物均为结直肠癌术后肠内营养不耐受的危险因素,添加膳食纤维是肠内营养不耐受的保护因素。基于各项影响因素构建列线图预测模型,经验证,模型C指数为0.808,一致性较好;校准曲线显示该模型具有较好的准确性。列线图模型预测结直肠癌术后肠内营养不耐受的ROC曲线下面积为0.823(95% CI:0.760~0.885),该模型具有良好的区分度。 结论 基于年龄、营养风险等影响因素构建的列线图预测模型具有良好的区分度和一致性,可作为临床预测结直肠癌患者术后肠内营养不耐受的有效工具。 Abstract:Objective To develop a nomogram for predicting the risk of enteral nutrition intolerance after colorectal cancer surgery and to preliminarily validate the predictive performance. Methods A retrospective analysis was conducted on 185 colorectal cancer patients who underwent surgical treatment at the General Hospital of Eastern Theater Command from January 2021 to June 2024. All patients received postoperative enteral nutrition support. Based on the presence of intolerance symptoms, patients were divided into the tolerance group (n=129) and the intolerance group (n=56). The clinical data of the two groups were collected, including demographic indicators, colorectal cancer conditions, surgical data, and postoperative enteral nutrition-related conditions. Multivariate logistic regression analysis was used to identify the influencing factors for postoperative enteral nutrition intolerance. A nomogram prediction model was then constructed based on these factors. The discrimination and calibration of the model were verified by the receiver operating characteristic (ROC) curve and calibration curve. Results Advanced age, presence of nutritional risk, postoperative bed rest time ≥ 3 days, initiation of enteral nutrition ≥ 48 hours, and use of analgesic drugs were identified as risk factors for postoperative enteral nutrition intolerance, while dietary fiber supplementation was a protective factor. A nomogram model incorporating these variables was developed. The model demonstrated good discrimination, with a C-index of 0.808. The calibration curves showed good agreement between predicted and observed outcomes. The AUC for the nomogram predicting postoperative enteral nutrition intolerance in colorectal cancer was 0.823 (95% CI: 0.760-0.885), indicating satisfactory predictive efficacy. Conclusion The nomogram prediction model constructed based on influencing factors such as age and nutritional risk demonstrates good discrimination and consistency, and can serve as an effective tool for predicting postoperative enteral nutrition intolerance in colorectal cancer patients. -
Key words:
- Colorectal cancer /
- Surgery /
- Enteral nutrition /
- Intolerance /
- Nomogram
-

图 1 结直肠癌术后肠内营养不耐受的列线图预测模型
Figure 1. Nomogram prediction model for enteral nutrition intolerance after colorectal cancer surgery

图 3 列线图模型预测结直肠癌术后肠内营养不耐受的ROC曲线
Figure 3. ROC curve analysis of the nomogram prediction model for enteral nutrition intolerance after colorectal cancer surgery
表 1 结直肠癌术后肠内营养不耐受的单因素分析
Table 1. Univariate analysis of enteral nutrition intolerance after colorectal cancer surgery
项目 耐受组(n=129) 不耐受组(n=56) 统计量 P值 性别[例(%)] 0.016a 0.900 男性 75(58.14) 32(57.14) 女性 54(41.86) 24(42.86) 年龄[M(P25,P75), 岁] 60.0(53.0, 65.0) 66.5(60.0, 73.0) 4.949b <0.001 营养风险[例(%)] 5.970a 0.015 有 11(8.53) 12(21.43) 无 118(91.47) 44(78.57) 肿瘤部位[例(%)] 0.057a 0.811 结肠 83(64.34) 35(62.50) 直肠 46(35.66) 21(37.50) 肿瘤直径[M(P25,P75), cm] 3.2(2.3, 4.8) 3.7(2.5, 4.9) 1.042b 0.298 肿瘤分化程度[例(%)] 0.258b 0.796 低分化 61(47.29) 26(46.43) 中分化 35(27.13) 14(25.00) 高分化 33(25.58) 16(28.57) TNM分期[例(%)] 0.136a 0.713 Ⅰ~Ⅱ 82(63.57) 34(60.71) Ⅲ~Ⅳ 47(36.43) 22(39.29) 淋巴结转移[例(%)] 0.002a 0.961 是 35(27.13) 15(26.79) 否 94(72.87) 41(73.21) 手术方式[例(%)] 0.015a 0.903 腹腔镜手术 91(70.54) 40(71.43) 开腹手术 38(29.46) 16(29.57) 手术时间[M(P25,P75), min] 159.00(132.00, 186.00) 165.00(149.25, 188.00) 1.604b 0.109 平均动脉压[M(P25,P75), mmHg] 96.0(88.0, 104.0) 94.5(87.0, 102.0) 1.192b 0.233 术后卧床时间[例(%)] 4.805a 0.028 <3 d 71(55.04) 21(37.50) ≥3 d 58(44.96) 35(62.50) 肠内营养方式[例(%)] 0.212a 0.899 经口 45(34.88) 21(37.50) 鼻饲置管 60(46.51) 24(42.86) 造瘘 24(18.60) 11(19.64) 肠内营养开始时间[例(%)] 4.942a 0.026 <48 h 69(53.49) 20(35.71) ≥48 h 60(46.51) 36(64.29) 肠内营养配方[例(%)] 0.038a 0.846 整蛋白型 81(62.79) 36(64.29) 短肽型或氨基酸型 48(37.21) 20(35.71) 添加膳食纤维[例(%)] 8.742a 0.003 有 81(62.79) 22(39.29) 无 48(37.21) 34(60.71) 添加益生菌[例(%)] 0.050a 0.822 有 53(41.09) 24(42.86) 无 76(58.91) 32(57.14) 使用抗菌药物种类[例(%)] 0.213a 0.644 1种 83(64.34) 38(67.86) ≥2种 46(35.66) 18(32.14) 使用促胃动力药物[例(%)] 0.070a 0.791 是 58(44.96) 24(42.86) 否 71(55.04) 32(57.14) 使用镇痛类药物[例(%)] 8.165a 0.004 是 25(19.38) 22(39.29) 否 104(80.62) 34(60.71) 注:a为χ2值,b为Z值;1 mmHg=0.133 kPa。  下载: 导出CSV
表 2 变量赋值情况
Table 2. The assignment situation of independent variables
变量 赋值方法 年龄 连续型变量,以实际值赋值 营养风险 无=0,有=1 术后卧床时间 <3 d=0,≥3 d=1 肠内营养开始时间 <48 h=0,≥48 h=1 添加膳食纤维 无=0,有=1 使用镇痛类药物 否=0,是=1
下载: 导出CSV
表 3 结直肠癌术后肠内营养不耐受的多因素logistic回归分析
Table 3. Multivariate logistic regression analysis of postoperative enteral nutrition intolerance after colorectal cancer surgery
变量 B SE Waldχ2 P值 OR值 95% CI 年龄 0.130 0.028 21.540 <0.001 1.139 1.078~1.203 有营养风险 1.177 0.536 4.824 0.028 3.245 1.135~9.275 术后卧床时间≥3 d 1.014 0.394 6.617 0.010 2.755 1.273~5.964 肠内营养开始时间≥48 h 0.753 0.333 5.113 0.024 2.123 1.106~4.077 添加膳食纤维 -0.881 0.379 5.396 0.020 0.414 0.197~0.871 使用镇痛类药物 0.990 0.353 7.877 0.005 2.692 1.348~5.375
下载: 导出CSV
-
[1] ZHENG R S, ZHANG S W, ZENG H M, et al. Cancer incidence and mortality in China, 2016[J]. J Natl Cancer Cent, 2022, 2(1): 1-9. [2] BRAY F, LAVERSANNE M, SUNG H, et al. Global cancer statistics 2022: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries[J]. CA Cancer J Clin, 2024, 74(3): 229-263. [3] 张丽华, 张莉, 张丽萍, 等. 脓毒症患者肠内营养喂养不耐受现况及影响因素研究[J]. 华南预防医学, 2023, 49(2): 174-178.ZHANG L H, ZHANG L, ZHANG L P, et al. Enteral nutrition feeding intolerance and its influencing factors in patients with sepsis[J]. South China Journal of Preventive Medicine, 2023, 49(2): 174-178. [4] 中华医学会外科学分会结直肠外科学组, 张忠涛, 董明, 等. 中国结直肠癌手术病人营养治疗指南(2025版)[J]. 中国实用外科杂志, 2025, 45(2): 137-148.The Colorectal Surgery Group of the Surgical Branch of the Chinese Medical Association, ZHANG Z T, DONG M, et al. China nutritional therapy guidelines for colorectal cancer surgery patients(2025 edition)[J]. Chinese Journal of Practical Surgery, 2025, 45(2): 137-148. [5] BUKOWSKI J S, DEMBIÑSKI, DZIEKIEWICZ M, et al. Early enteral nutrition in paediatric acute pancreatitis: a review of published studies[J]. Nutrients, 2022, 14(16): 3441. DOI: 10.3390/nu14163441. [6] 倪荣, 陈颖颖, 左玲, 等. 危重患者肠内营养喂养不耐受现况及影响因素研究[J]. 华南预防医学, 2022, 48(9): 1140-1142.NI R, CHEN Y Y, ZUO L, et al. Status and influencing factors of enteral nutrition intolerance in critically ill patients[J]. South China Journal of Preventive Medicine, 2022, 48(9): 1140-1142. [7] VAN SMEDEN M, REITSMA J B, RILEY R D, et al. Clinical prediction models: diagnosis versus prognosis[J]. J Clin Epidemiol, 2021, 132: 142-145. doi: 10.1016/j.jclinepi.2021.01.009 [8] 中华人民共和国国家卫生健康委员会. 中国结直肠癌诊疗规范(2020年版)[J]. 中华外科杂志, 2020, 58(8): 561-585.The National Health Commission of the People's Republic of China. Protocol of Diagnosis and Treatment of Colorectal Cancer(2020 edition)[J]. Chinese Journal of Surgery, 2020, 58(8): 561-585. [9] REINTAM BLASER A, DEANE A M, PREISER J C, et al. Enteral feeding intolerance: updates in definitions and pathophysiology[J]. Nutr Clin Pract, 2021, 36(1): 40-49. doi: 10.1002/ncp.10599 [10] JENKINS B, CALDER P C, MARINO L V. A systematic review of the definitions and prevalence of feeding intolerance in critically ill adults[J]. Clin Nutr ESPEN, 2022, 49: 92-102. doi: 10.1016/j.clnesp.2022.04.014 [11] 钟明霞, 傅聿铭, 吴万庆, 等. 早期肠内营养对结肠癌根治术后患者营养状态及消化道功能恢复的影响[J]. 癌症进展, 2020, 18(3): 317-320.ZHONG M X, FU Y M, WU W Q, et al. The effect of early enteral nutrition on the nutritional status and recovery of gastrointestinal tract function in patients with radical colectomy[J]. Oncology Progress, 2020, 18(3): 317-320. [12] 赵敏, 桑畅野, 闫长红. EEN+PN方案对直肠癌根治术围手术期患者营养和免疫指标及康复的影响[J]. 中华全科医学, 2022, 20(9): 1587-1589, 1611. doi: 10.16766/j.cnki.issn.1674-4152.002655ZHAO M, SANG C Y, YAN C H. Effect of EEN and PN scheme on the nutrition indicators, immunological function and rehabilitationin patients undergoing laparoscopic colorectal surgery[J]. Chinese Journal of General Practice, 2022, 20(9): 1587-1589, 1611. doi: 10.16766/j.cnki.issn.1674-4152.002655 [13] 赵成, 胡丽娜, 喻慧, 等. 肠内营养支持对转移性结直肠癌患者生存质量及疗效的影响分析[J]. 中华内分泌外科杂志(中英文), 2024, 18(4): 578-582.ZHAO C, HU L N, YU H, et al. Effect of enteral nutrition support on quality of life and therapeutic effect in patients with metastatic colorectal cancer[J]. Chinese Journal of Endocrine Surgery, 2024, 18(4): 578-582. [14] STANNARD D. Early enteral nutrition within 24 hours of lower gastrointestinal surgery versus later commencement for length of hospital stay and postoperative complications[J]. J Perianesth Nurs, 2020, 35(5): 541-542. doi: 10.1016/j.jopan.2020.07.003 [15] WANG W Y, CHEN C W, WANG T J, et al. Outcomes of early enteral feeding in patients after curative colorectal cancer surgery: a retrospective comparative study[J]. Eur J Oncol Nurs, 2021, 54: 101970. DOI: 10.1016/j.ejon.2021.101970. [16] 曾佳琪, 张博, 苏红辉. 口腔颌面部恶性肿瘤患者肠内营养喂养不耐受状况及影响因素[J]. 南方医科大学学报, 2021, 41(7): 1114-1118.ZENG J Q, ZHANG B, SU H H. Incidence of enteral feeding intolerance and its risk factors in patients with oral and maxillofacial malignancies[J]. Journal of Southern Medical University, 2021, 41(7): 1114-1118. [17] ZHANG Y N, MA D D, LANG B, et al. Effect of opioid-free anesthesia on the incidence of postoperative nausea and vomiting: a meta-analysis of randomized controlled studies[J]. Medicine, 2023, 102(38): e35126. DOI: 10.1097/MD.0000000000035126. [18] XIAO Y J, XU L. Prevalence and risk factors of enteral feeding intolerance in critically ill patients and the effectiveness of preventive treatments: a prospective study[J]. Saudi J Med Med Sci, 2023, 11(2): 135. DOI: 10.4103/sjmms.sjmms_384_22.
 点击查看大图
计量
- 文章访问数: 11
- HTML全文浏览量: 4
- PDF下载量: 1
- 被引次数: 0
